๐Ÿ”

Dr Iliana9 Group

๐Ÿ‘ 25
๐Ÿ‡ฒ๐Ÿ‡ฆ Malaysia ๐Ÿ‡ฒ๐Ÿ‡ช Melayu Kawan & Komuniti Telegram

โ€œDr saya nak tanya apa tugas HO dalam #OT (operation theatre)? ๐Ÿ˜ท

Contohnya, apa yg HO boleh buat waktu assist #LSCS?โ€ ๐Ÿค”
.

Learn what you need to know in this FREE online course;

https://medicorp-class.teachable.com/courses/ho-role-in-ot-0822

๐Ÿ‘‰๐Ÿป HO role in assisting #surgery; what to do before, during & after surgery?

๐Ÿ‘‰๐Ÿป common #mistakes to avoid while assisting operation

๐Ÿ‘‰๐Ÿป Modified ISBAR formula to #book_case for operation from anaest team (with practice)

All the best ๐Ÿ’ช๐Ÿป

โœˆ๏ธ Telegram Join

Subscriber Growth

14,846Subscribers
74Posts
3.26KPhotos
160Videos
1.4KLinks
255Files

Latest Telegram Posts

Dr Iliana9 Group
26 Jul, 21:03
What's wrong with this patient?

What can we do to prevent this in the future? ๐Ÿค”
Dr Iliana9 Group
23 Jul, 18:58
Download HO #logbooks here,

& get to know all the compulsory topics & procedures for HO in each posting;

https://t.me/+zt4DsADauzdhZjE1
Dr Iliana9 Group
22 Jul, 14:59
Wondering what to revise before starting HOship soon? ๐Ÿค”

Download Ampang HO guide for FREE here; https://t.me/nota_perubatan/164
Dr Iliana9 Group
20 Jul, 16:55
Dr Iliana9 Group
19 Jul, 15:44
Attention to all HOs included in HO Intake Bil 4/2026, if you wish to;

๐Ÿ‘‰ get access to senior HOs WA #group of your hosp

๐Ÿ‘‰ join FREE online Mentorship revision with Dr Iliana,
.

Join live Mentorship revision #briefing this Tuesday, 21st June at 9 PM to 10 PM ๐Ÿ˜‡
.

Register for ๐Ÿ†“ for the revision here;
https://medicorp.onpay.my/order/form/mentorshiprevision0726
Dr Iliana9 Group
15 Jun, 23:16
Just graduated?

Already choose your hosp via E-HO?

Finishing your current posting & will transfer out to new department soon?


But unsure what to #expect & prepare for the next posting, or HOship as general?


Enroll for free to #Departmental Welcoming session NOW at Medicorpโ€™s Teachable school; https://medicorp-class.teachable.com

You will learn;

โœ… HO role in each posting,

โœ… must-know #diseases for each posting; the common cases & #emergencies

โœ… few case discussions as kickstart #revision for each posting!
Dr Iliana9 Group
15 Jun, 09:16
Dr Iliana9 Group
15 Jun, 09:16
โฌ†๏ธ Normal labour & #management of each stages

Ref; Kedah O&G protocol
Dr Iliana9 Group
15 Jun, 09:16
So today we'll focus on management of 1st stage of labour ie intrapartum management;

All these plan are HO #responsibilities at PAC, antenatal wards & LR (labour room)
Dr Iliana9 Group
15 Jun, 09:16
๐ŸคฐIntrapartum management
(during 1st stage of labour)

๐ŸŒŸaccording to VenOMMS ๐ŸŒŸ


1๏ธโƒฃ Plot #partogram & T/O LR

[Ventilation]


[Oral intake] ๐Ÿ”ฝ๐Ÿ”ฝ๐Ÿ”ฝ

2๏ธโƒฃ Allow sips of CF (clear fluids)

3๏ธโƒฃ Insert large bore branula & start IVD NS/HM/Dextrose Saline; 125cc/hour

โ—๏ธIn PIH patient; only 1cc/kg/hr (risk for APO) & use only NS โ€ผ๏ธ

โ—๏ธIn Diabetic patients; if DXT less than 7mmol/litre, use D5% solution instead of NS โ€ผ๏ธ


[Monitoring] ๐Ÿ”ฝ๐Ÿ”ฝ๐Ÿ”ฝ

4๏ธโƒฃ V/S monitoring hourly

โœ”๏ธIf PIH in crisis, every 15-30 mins
โœ”๏ธadd on GM monitoring in GDM patients


5๏ธโƒฃ CTG #monitoring (tracing on admission & post ARM), then to repeat accordingly based on risk factor

6๏ธโƒฃ Time #contraction; aim good contraction (4:10 in primid, 3:10 in multipara)

7๏ธโƒฃ NRVE in ? hour (according to current V/E findings)

8๏ธโƒฃ 1 to 1 care (if enough LR personnel)

9๏ธโƒฃ Husband/#companion to accompany during labour (not available during pandemic ๐Ÿ˜ท )


[Medication] ๐Ÿ”ฝ๐Ÿ”ฝ๐Ÿ”ฝ

๐Ÿ”Ÿ #Analgesia if strong contraction

1๏ธโƒฃ1๏ธโƒฃ For Pitocin #augmentation 1 or 2 hour post ARM if contraction inadequate ( <4:10 in primid, <3:10 in multipara)

1๏ธโƒฃ2๏ธโƒฃ DIK regime (for GDM patients)


[Special Order] ๐Ÿ”ฝ๐Ÿ”ฝ๐Ÿ”ฝ

1๏ธโƒฃ3๏ธโƒฃ Amniotomy ie #ARM (if membrane intact)

Source;ย  โค๏ธ Medicorpโ€™s O&G #online courseโ—๏ธlocal LR protocol varies
Dr Iliana9 Group
15 Jun, 09:16
Compulsory #cases ie topics that HO need to know in O&G posting.
.

As medical grads waiting for HOship, focus on the ๐ŸŸฃ highlighted topics as your #preparation for O&G posting soon โ€ผ๏ธ
.

You can refer each topic in any of the O&G #protocols earlier ๐Ÿ˜‰
Dr Iliana9 Group
15 Jun, 09:16
Let's start our #revision on common topics in Obstetrics ๐Ÿคฑ

โ€ผ๏ธ Stages of Labour,
& definition of each stages

Wajib hafal โ€ผ๏ธ
Dr Iliana9 Group
08 Jun, 15:09
7Ps for #Intubation.

Kalau korang nak intubate patient, biasanya MO akan tanya fasal 7Ps ni.

Kalau tak tahu, melepaslah peluang nak intubate patient sebab kita tak tahu details about that procedures ๐Ÿ˜…


Nak belajar lebih lanjut tentang #intubation & post intubation care?

Jom praktis sama-sama di Clinical Skills #Workshop Medicorp; 17+3 procedures in 1 day โค๏ธ
Dr Iliana9 Group
02 Jun, 18:17
The clinical depth here be it managing complex disease, late presentations, and resource-constrained decision-making has shaped who we are as clinicians. For some, that creates a deep sense of responsibility to continue contributing within the same system.

Not everyone will feel this way. Some will leave and grow in different systems, and that path deserves respect.
But choosing to work within the system and remain should also be respected.
Because staying is not about settle up.
It can reflect a belief that this country, despite its flaws, remains a place worth serving, worth improving, and worth building a future in.

And sometimes, it is simply recognising that what we already have here is enough to keep us established.

At the same time, as pressure continues to build across all levelsโ€ฆ from HO to MO, specialists, and consultants. Thus, the stakeholders, our leaders.... should continue to review how to firmly supports and retains its healthcare workforce.

This also calls for addressing structural challenges within the system particularly bottlenecks in career progression at the specialist/consultant level, clearer role definition to prevent task spillover of other problematic supporting staffs and uneven workload distribution, and more meaningful opportunities for advancement into higher-paying roles that are appropriately benchmarked against comparable specialist/consultant positions elsewhere.

Perhaps it is also worth speaking directly to those at the beginning of this journey... to medical students, HO, and young MO navigating these early decisions.
It is understandable to feel uncertain in the current climate. The surrounding conversations can be intense, and at times, discouraging.
But before deciding too early, allow yourself the space to experience the system for what it isโ€ฆ
not only through what is said about it.

We definitely will encounter pressure, but also encounter room of growth. The exposure to complexity, the responsibility carried, and the pace of learning within the public system continue to offer a depth of experience.

Many who have trained within this environment recognise its role in shaping clinical judgement, resilience, and professional identity.
We do not have to commit to one path indefinitely. But giving yourself time to build a strong foundation as a doctor.
The decision to stay or leave will eventually take its own course. But the foundation built during this phase often becomes the reference point for whatever direction you eventually choose.

My humble opinion.
DrAnorHidayah
Dr Iliana9 Group
02 Jun, 18:17
Becoming a doctor is one thing. Choosing to stay in a public hospital is another.

There has been a growing culture of dissatisfaction surrounding work in the public service of healthcare system. The concerns of high workload, system pressures, career uncertainties, and the blurred expectations of covering multiple roles are real. Yet, the overall tone of the conversation has gradually shifted, where staying in MOH is sometimes framed less as an active choice and more as something one simply remains in.

And lately, there has been increasing discussion about recruitment from neighbouring countries, with doctors and paramedics drawn across the border by better pay and seemingly more efficient systems. It is understandable why many consider it.

But for some of us, the old saying still holds meaning: hujan emas di negeri orang, hujan batu di negeri sendiri lebih baik di negeri sendiri.

Yes. it is increasingly challenging with growing rate of burnout with overwhelming cases and tasks. But sometimes meaning is not measured solely by salary or system efficiency.
For some of us, we choose to be thereโ€ฆ
I wonโ€™t say the doubts arenโ€™t there. but for now.. here we are. Trying to make sense of it, trying to find footing within the system rather than stepping away from it

The public system offers something difficult to replicate elsewhere --- depth of clinical exposure, particularly in high-acuity and facilities, patients loads and complex cases. Nowhere else will you manage such a breadth of pathology, often at advanced stages, while carrying real responsibility early in career.
That high stake environment accelerates maturation not only technically, but in judgement, prioritisation, and resilience.

Beyond that, there is continuity in training and subspecialty development. MOH remains one of the few ecosystems where structured progression from HO to MO, through specialist be it parallel or MMED training, and onward to subspecialty and consultant level remains accessible without the fragmentation often seen in other pathways.

Then there is something less visible, but equally important: Purpose. Public healthcare places you at the centre of need. You treat patients because they require care. Can they afford options?. That by some means shapes a different kind of doctor.

Of course, many leave and for valid reasons. Better pay, improved work-life balance, or different career goals. These are legitimate decisions. But the fact that many still choose to join and stay should not be dismissed as a lack of options. More often, it reflects a different set of priorities.

Staying in MOH can mean choosing long-term growth over short-term comfort. It can mean valuing exposure, training, and impact over immediate financial gain. It can also mean believing that the system, despite its flaws, is still worth contributing to and improving from within.

Not every path needs to converge.
What matters is recognising that remaining is not passivity.
At the same time, we are not immune to the pressure. We hear the same conversations, we see the same frustrations, and there are moments when we question our own position.

But holding a firm decision does not mean closing all other doors.
"Keep he option open" sais my friend long time ago. Not because we are uncertain, but because we understand that circumstances can change.
A significant reason, a shift in priorities, or a new opportunity may alter the course.
For now, many of us remain because our reasons are still stronger than our doubts.
And perhaps that is the most honest place to stand not in blind loyalty, and not in reactionary escape, but in a conscious, ongoing decision base on calculated risk in every direction.

Staying isnt easy even until now continuing my journey in subspeciality training.

Public healthcare service in Malaysia, with all itโ€™s imperfections, has given us something more valuable: our training, our exposure, our patients, and our growth. Not to forget with so many inspiring teachers who dedicate their expertise in public service.
Dr Iliana9 Group
02 Jun, 17:17
Dr Iliana9 Group
26 May, 17:45
More must know X-ray for HOs

& common #abnormalities that HO need to be able to detect;
.

on โœ… #Abdominal x-ray;

โ—PGU (perforated gastric ulcer)

โ—IO (small & large bowel obstruction)

โ—kidney & ureteric stone
.

on โœ… #Hip xray;

โ—Pelvic #factures

โ—NOF (neck of femur fractures)

Learn more about identifying pelvic & NOF fractures at Medicorp's #online Orthopaedic course;

http://medicorp-class.teachable.com/p/orthopaedic_onlinecourse
Dr Iliana9 Group
26 May, 17:45
Must know CXR #interpretation for HOs โ€ผ๏ธ


6 Common abnormalities any HO must be able to detext on CXR;

๐Ÿ›‘ cardiomegaly ๐Ÿซ€

๐Ÿ›‘ pneumothorax

๐Ÿ›‘ pleural effusion

๐Ÿ›‘ acute pulmonary edema

๐Ÿ›‘ lung infection ie lobar pneumonia ๐Ÿซ

๐Ÿ›‘ PTB changes
Dr Iliana9 Group
26 May, 17:44
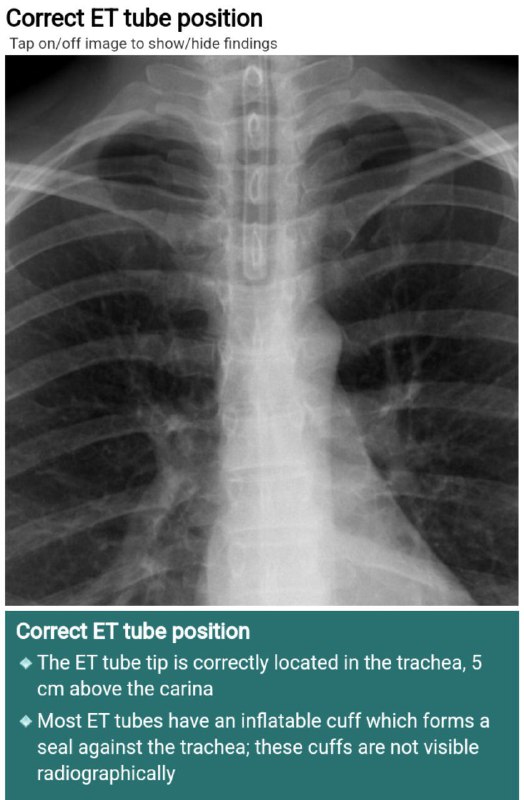
"Doktor, ini chest X ray post intubation patient katil 2 tadi"

What to look for in post intubation CXR?
- To look for complication, especially pneumothorax
- To confirm placement of endotracheal tube

The position of tip of ETT should be 5-7 cm above the carina in the neutral position of neck. When the carina is not visible, the tip of the ET tube should lie over the second to fourth thoracic vertebrae (T2-T4) or at the level of medial ends of the clavicles as carina is located between T5 and T7.ย 

Further reading:
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4173625

https://www.radiologymasterclass.co.uk/tutorials/chest/chest_tubes/chest_xray_et_tubes_anatomy#top_2nd_img

#ED
@nota_perubatan

Related Groups